

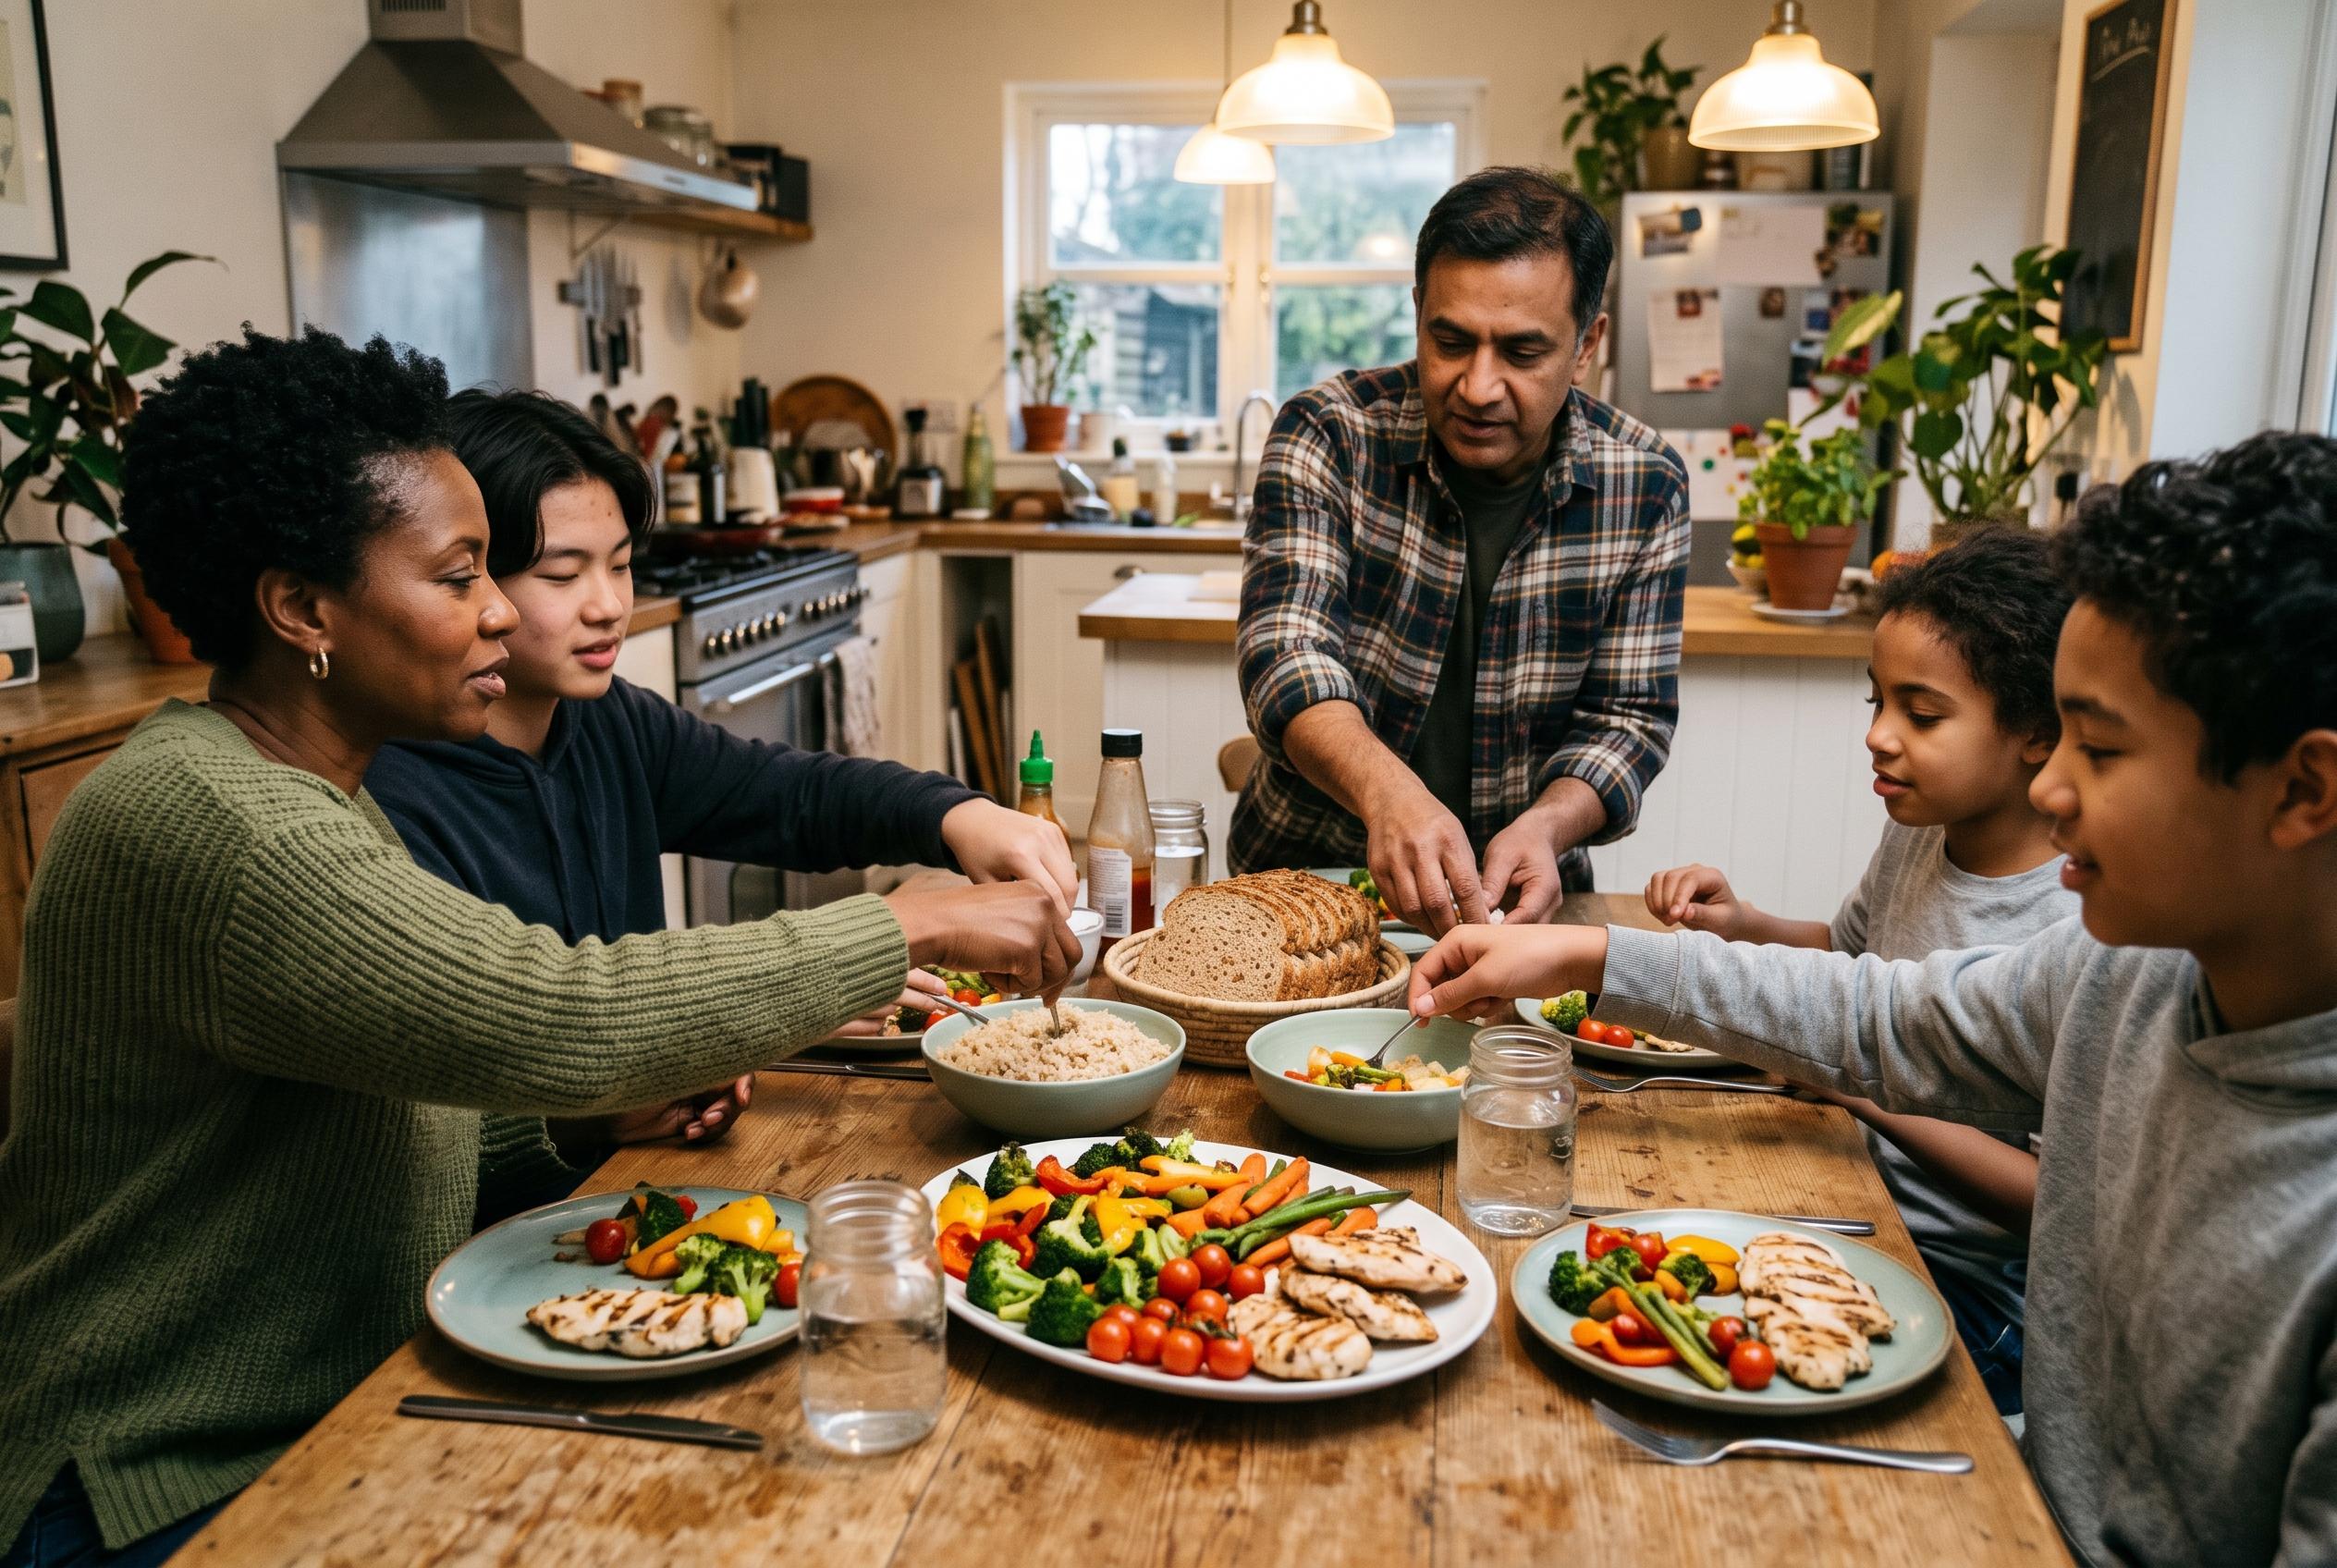

Studies suggest that putting vegetables and protein before bread, rice or pasta may reduce short-term glucose spikes, but researchers say the long-term benefits remain unproven.
A growing body of research suggests that the order in which foods are eaten may matter almost as much as the foods themselves, at least when it comes to blood sugar control. The idea, often called meal sequencing or food order, is simple: begin with vegetables or other fibre-rich foods, move on to protein and fat, and leave starchy carbohydrates such as bread, rice or pasta until last. According to the lead article, recent laboratory work from Kyoto University has added a new twist by suggesting that fat consumed before glucose can dampen the earliest rise in blood sugar, at least in mice.
The attraction of this approach is that it does not require people to change what is on the plate, only the sequence in which it is eaten. Earlier human studies have pointed in the same direction. In a small trial published in Diabetes Care, researchers found that people with type 2 diabetes who ate vegetables and protein before carbohydrates had markedly lower post-meal glucose spikes than when they ate in the reverse order. A separate study in BMJ Open Diabetes Research & Care reported a similar pattern, with the glucose curve falling by roughly half when chicken and vegetables were eaten before bread and juice. Research in Diabetologia also found that eating fish before rice slowed stomach emptying and increased GLP-1, one of the gut hormones involved in insulin release and satiety.
Those results fit with the biology of digestion. Fibre-rich vegetables can slow the movement of food through the stomach, while protein and fat tend to delay gastric emptying and stimulate incretin hormones such as GLP-1 and GIP. These hormones help prompt insulin release and can blunt the speed at which glucose enters the bloodstream. The lead article also notes a role for glucagon and the vagus nerve, which together may form a redundant signalling network linking the gut and brain. The new Kyoto work, carried out in mice, suggests that this network can be activated when fat arrives before carbohydrate, delaying glucose absorption and softening the early post-meal surge.
Still, the evidence has important limits. A systematic review and meta-analysis indexed on PubMed Central found that carbohydrate-later meal patterns may lead to little or no meaningful change in HbA1c, the longer-term blood sugar marker, and no clear difference in glucose, insulin or incretin measures two hours after meals. The authors said the approach should not be given priority over standard dietary advice without stronger evidence from larger, better-designed trials. Other research has also shown that meal size, meal timing and the composition of earlier meals can change post-meal glucose responses, which makes it difficult to isolate sequence alone as the decisive factor.
That is why the most sensible reading of the research is cautious rather than revolutionary. For people with diabetes or prediabetes, starting with salad or vegetables, then eating protein, and finishing with starches is a low-risk habit that may help reduce sharp glucose peaks. It is not a cure, and it is not a substitute for medication, weight management or overall carbohydrate control. But the pattern is plausible, easy to try and increasingly backed by short-term human evidence, even if the long-term benefit remains unproven. The Kyoto mouse study adds mechanistic support, but it does not yet show that swapping the order of a meal will deliver the same effect in people eating ordinary mixed dishes.
For now, meal sequencing sits in an interesting middle ground: promising enough to deserve attention, but not strong enough to become a firm clinical rule. The strongest case for it is practical rather than dramatic. If someone is already building a balanced meal, starting with vegetables and protein before moving to carbohydrates may modestly improve the blood sugar response without requiring a new diet altogether. What the research has not yet shown is that this simple adjustment can meaningfully change long-term outcomes on its own.
Disclaimer: This content is for informational purposes only and is not intended to be a substitute for professional medical judgment, advice, diagnosis, or treatment.



